When I first started learning effective communication skills, I developed little equations in my head to help me construct a self-disclosure message, an active listening response, or a confrontative I-message.
These little equations became a way of training my brain. With practice, the steps became familiar, and eventually the communication skills became more natural and automatic.
I often work with clients and couples who have great difficulty recognising their feelings and needs, let alone finding the words to express them. This is where a few simple, repeatable steps can be incredibly helpful. We can literally train the brain to develop new neural pathways and create new habits for how we communicate.
And it starts with self-empathy.
Self-Empathy
Self-empathy means turning your attention inward and becoming curious about what is happening for you.
You might ask yourself:
What am I feeling?
What is happening for me right now?
What need is underneath this reaction?
What am I wanting, valuing or longing for?
Before we can communicate effectively with another person, we need some capacity to understand ourselves.
Many people try to communicate their experience without having a vocabulary for what they are actually feeling or needing. Instead, they jump straight to explaining what the other person is doing wrong.
“You never listen to me.” “You don’t care.” “You’re so selfish.”
These statements may express distress, but they don’t necessarily reveal what is happening inside us or the need that is trying to be met, or how the other’s behaviour is effecting us. Instead they create conflict as they are ‘YOU’ messages and the brain perceives this as a threat.
Self-empathy gives us the opportunity to pause and discover what is underneath the reaction.
What am I feeling? What do I need?
Once we have some clarity, we can begin to share that experience with another person.
Here is a feelings and needs list to support you to begin to familiarise yourself to expand from mad, sad and glad.
Self-Disclosure
Self-disclosure is the process of giving another person a glimpse into our internal world.
Using effectiveness training, self-disclosure is about communicating your own experience rather than making the other person the problem.
A powerful shift that builds relationships.
Have you ever noticed how interested and connected your partner becomes when they get a genuine glimpse of what is happening inside you — particularly when they are not being blamed for it? There is something deeply connecting about being invited into another person’s inner world.
A Simple Self-Disclosure Equation
One little equation I use to help people practise this is:
I + feel + fact
For example:
“I get really excited when I am able to express myself clearly.”
Or:
“I am saddened when I’m not able to communicate what I need.”
The formula is simply a training tool. It helps you remember to speak from your own experience.
Be Careful With the Word “Feel”
An important part of learning self-disclosure is noticing whether the word feel is actually followed by a feeling.
For example:
“I feel that you are not listening to me.”
The word feel appears in the sentence, but there is no feeling being highlighted as well as “you are not listening to me” is actually an interpretation or judgement about the other person’s behaviour not the facts.
A fact is something you can see, hear or otherwise directly experience.
For example:
“When I we are talking and you looked at your phone, I am disappointed as I was eager to spend time with you”
Now we have:
Fact: Talking together, and looking at phone Feeling: disappointed and eager
The focus stays with my experience, rather than becoming an accusation about your intention. That way we don’t force the other into conflict and we still get to express our disappointment.
This small distinction can make a significant difference to how a message is received.
Train Your Brain
Communication is made of micro-skills that practiced over time changes the way we express ourself.
Try this simple exercise:
Send Three Self-Disclosure Messages Per Day
Share three genuine self-disclosure messages with someone each day.
They don’t have to be deep or complicated.
You might share:
“I’m really enjoying this coffee this morning with you.”
“I’m a little nervous about today’s presentation.”
“I’m really grateful that we’re having this time together.”
“I’m excited about what we’re planning together .”
“I’m tired and I need some quiet time this evening.”
If remembering is difficult, attach the practice to something you already do.
You could share your self-disclosure messages:
over your morning coffee
when you greet someone
when you send a text
when you arrive home
before going to bed
The more you practise noticing your internal experience and putting it into words, the easier it becomes.
You are not simply learning a communication technique.
You are training your brain to create a new way of relating.
And with practice, those little formulas can become something much more valuable than formulas.
They become capacity.
Capacity to know yourself. Capacity to express yourself. And ultimately, capacity to create deeper connection in your relationships.
The Game Changer in Relationships: Curiosity Over Justification
There is a moment in almost every relationship conflict when the conversation reaches a fork in the road. It may begin with a forgotten phone call, an impatient tone of voice, an unanswered text message or the familiar words:
“You never listen to me.”
In that moment, there are two very different paths available.
One path leads towards justification. The other leads towards curiosity.
The difference between them can determine whether two people move into conflict drift or create connection.
Most of us don’t consciously choose justification. It simply arises as a default as our brains are wired for war. As we read the signs, the sound of the voice, the frown, the eye roll and walking away our primitive parts of our brain engage and we go to war. Before we have even realised what is happening we start to defend ourself
“That’s not true.”
“I do listen.”
“You don’t understand how stressful my day was.”
“What about all the times I’ve been there for you?”
Suddenly, the conversation is no longer about understanding one another or taking care of the space in the middle, that couple bubble, that connection.
It becomes a courtroom. Each person presents evidence. Each person defends their intentions. Each person quietly hopes the jury will declare them innocent.
Yet relationships rarely heal because someone finally proves they were right. And if you are fighting about memory ie who said what when, they you are both right and both wrong!
We heal when someone becomes curious enough to ask,
“Tell me more.”
Why We Justify
Justification is rarely selfish or uncaring. Most often, it is psychobiological.
When we perceive we are being criticised, misunderstood or blamed, our sympathetic nervous system (fight and flight system) automatically prepares us for danger. Long before we consciously choose our response, our body has already begun responding as though we are under threat.
Our heart beats faster. Our breathing becomes shallow. Our muscles tighten. Stress hormones such as adrenaline and noradrenaline prepare us to defend ourselves. Then the cortisol clicks in! Our reptilian brains evolve over thousands of years, a response that helped our ancestors survive physical danger, engages!
Today, however, the greatest threats are often emotional.
A threat to our identity.
A threat to our belonging.
A threat to feeling loved.
A threat to believing we are enough.
So when a partner says,
“I felt hurt when you didn’t call,”
our nervous system may hear,
“You’re failing me.”
“You’re a terrible partner.”
“You’re letting me down.”
Without even realising it, we stop listening for understanding and begin listening for danger. The brain shifts from connection to protection.
The emotional centres responsible for detecting threat become highly active, while the prefrontal cortex—the part of the brain responsible for empathy, curiosity, perspective-taking and thoughtful decision-making—becomes less available.
We are no longer asking, “What is happening for my partner?”
Instead, our nervous system asks, “How do I protect myself?”
And so we justify.
“I was busy.”
“I told you I had meetings.”
“You know how stressful work has been.”
Everything we say may be true, but truth spoken from a defensive nervous system does not meet a need to be heard, understood, acknowledgement, for connection, for safety and care.
When Two Nervous Systems Go to War
The moment one person needs to be heard and isn’t, their nervous system becomes activated too.
They speak louder.
You defend yourself harder.
They become more emotional.
You become more certain.
They pursue.
You withdraw.
Or perhaps both of you fight.
The original issue quietly disappears beneath two nervous systems desperately trying to protect themselves as well as get their needs met!
What looked like an argument about dishes, money or a phone call has become something much deeper.
It has become two human beings asking silent questions.
Do I matter?
Am I safe with you?
Do you understand me?
Do I matter to you?
Will you reject me?
Will you choose me?
Genuine intimacy requires enough safety for people to remain present with themselves and with one another, even when difficult emotions arise. When the nervous system becomes overwhelmed, curiosity naturally narrows and self-protection takes over.
This is why telling your partner to “calm down” rarely works! Yet shifting gears to hear the need that is trying to be met does.
An activated nervous system cannot simply be reasoned into feeling safe. Sometimes healing begins by slowing everything down.
Breathing.
Softening our voice
Sitting down and facing each other
Waving the flag of friendliness before you go offline
Taking a break and coming back when regulated to discuss the issues
The Hidden Longing Beneath Every Argument
One of the greatest shifts whether we are a couple, a parent, a daughter, sibling, colleague or employer, we can make is learning to hear what sits beneath the words. Listening for feelings and needs trying to be met.
When someone says,
“You never help me,”
perhaps what they are really saying is, “I feel lonely and need support”
“You don’t care about me.”
may actually mean, “I want to matter to you”
“You’re always on your phone.”
may really be saying, “I miss connecting with you”
Justification responds to the accusation.
Curiosity listens for the longing, the feelings and needs.
This is why curiosity is so powerful as it maintains connection whilst taking care of the space in the middle and not default to pro-self.
Rather than asking, “How do I prove I’m right?” it quietly wonders,
“What pain am I hearing underneath these words? What need is trying to be met?”
Shifting Gears: From Defending to Listening
Curiosity is more than asking good questions. It is learning to shift gears.
When we become defensive, we naturally listen for mistakes in our partner’s story. We prepare our response before they have even finished speaking.
We interrupt.
We explain.
We defend.
Curiosity asks us to able to hold the tension enough to temporarily put our own story aside, for a moment, and become deeply interested in the others.
This is where active and empathetic listening become transformational.
Active listening means being present and feeding back the feelings and facts that are trying to be expressed.
Empathetic listening goes even deeper.
It listens for feelings and unmet needs embedded in the longing beneath the behaviour and words.
Instead of responding with defensiveness when you hear:
“You never listen,”
we begin by responding by saying
“It sounds like you are eager to be heard around this?”
Or
“Is it that you are anxious as you would really like to connect?”
Notice that none of these statements require agreement and there is no “I” as you have left the message with the other.
It is simply communicating to gain understanding first.
It is only after we have gained understanding of the other and we are on the right track not consumed by assumptions, do we gently offer our own experience in the form of feelings and needs.
“Thank you for sharing that. Would you be willing to hear my experience about the situation?”
This is one of the beautiful paradoxes of relationships.
The fastest way to be understood is often to help the other person feel understood first.
Your feelings matter equally. But two activated nervous systems cannot truly listen at the same time. Someone has to shift gears first.
Curiosity Is Not Surrender
Many people worry that curiosity means admitting they were wrong.
It doesn’t.
Curiosity is not agreement.
It is not accepting blame for something you didn’t do.
It is not tolerating abuse.
Curiosity simply says,
“Your experience matters enough for me to understand it before asking you to understand mine.”
There is enormous strength in that. Because when people feel emotionally safe, they naturally become more curious about us in return.
From Winning to Repair
Healthy relationships are not built because we avoid conflict. They are built because we learn to repair after conflict., and quickly.
Repair begins when we recognise that intention and impact are often different. You may never have intended to hurt someone. Yet they may still have experienced hurt.
One simple sentence can change the entire direction of a conversation.
“It looks like that really upset you?”
That is not admitting malicious intent. It is acknowledging another person’s reality. And sometimes that is all the nervous system needs to begin relaxing.
Protecting the Relationship Instead of Protecting Yourself
The next time conflict begins, notice the moment you feel the urge to defend yourself.
Pause. Get curious!
Take one slow breath.
Notice your body.
Then ask yourself one question.
“Am I trying to protect my position, or am I trying to protect this relationship?”
Transformation does not emerge through pressure or persuasion, it emerges with tiny habits and grows from presence and emotional safety. It grows when curiosity becomes stronger than justification.
Because perhaps the greatest act of love is not having the perfect answer. It is having the courage to remain curious.
To listen before explaining.
To understand before correcting.
To reflect before reacting.
To protect the relationship before protecting your ego.
So before saying,
“But…”
pause. Ask,
“Help me understand what is going on for you.”
Listen for the feelings.
Listen for the needs.
Listen for the longing beneath the words and behaviour.
Then, once the other knows they have been heard, gently share your own heart.
Because love is rarely strengthened by proving who was right. It is strengthened when two people feel safe enough to stop defending themselves and begin discovering one another again.
That is the quiet power of curiosity.
And sometimes, it is the doorway that leads two people home to each other, to security, mutuality and respect.
Judy walked into my room clinging tightly to the arm of her partner. A tall, elegant woman of 69, she appeared frightened, vague and uncertain. She sat down without letting go of him. I noticed immediately her dependence on him and his apparent impatience with that dependence. Each time he shifted away, she reached for him again. Judy had brought him for support, but it quickly became clear that his presence was not helping her feel safe.
Judy had been referred to me by a local wellness clinic. More than ten years earlier, she had been prescribed Cymbalta (duloxetine), a serotonin-norepinephrine reuptake inhibitor (SNRI), by her psychiatrist.
SNRIs are based on the “monoamine hypothesis” of depression. They work by blocking the serotonin transporter (SERT) and norepinephrine transporter (NET), theoretically increasing signalling in parts of the brain involved in mood, attention and pain regulation. However, despite decades of use, the precise mechanisms of antidepressants and antipsychotics remain poorly understood.
Judy had originally been prescribed 30 mg of Cymbalta. Several years earlier she had attempted to discontinue the medication and had successfully reduced to 5 mg. However, she dropped from 5 mg to zero too quickly and experienced severe withdrawal symptoms. Feeling “awful,” she returned to her doctor, who reinstated Cymbalta at 60 mg before later reducing it to 30 mg and adding Lexapro (escitalopram), an SSRI, to “assist” the withdrawal process.
Her pharmacist raised concerns about serotonin syndrome, which caused Judy considerable anxiety. Serotonin syndrome is a potentially serious reaction caused by excessive serotonin activity, usually when multiple serotonergic medications are combined. Ironically, while stopping psychiatric medication too abruptly can be dangerous, adding medications can also create complications.
This uncertainty led Judy to compulsively research her symptoms online using ChatGPT and other sources, which only intensified her fear.
What Judy was actually experiencing was a combination of rapid withdrawal from psychotropic medication, multiple interacting prescriptions, escalating anxiety, poor sleep and eventually akathisia.
Akathisia is a movement disorder characterised by an intense inner restlessness and an overwhelming urge to move. Although not life-threatening, it can be profoundly distressing and may contribute to agitation, despair and suicidal thinking.
Neuroadaptation and Withdrawal
Over the years Judy’s brain had adapted to the medications she was taking. This process, known as neuroadaptation, involves changes in receptor sensitivity and neurotransmitter regulation. When medications are withdrawn too quickly, the nervous system can become destabilised.
Judy had experienced this before. In her twenties, after treatment for anorexia, she had abruptly stopped antidepressants and experienced withdrawal symptoms. Years later, when she attempted to stop Cymbalta rapidly under medical guidance, she again experienced severe withdrawal.
Unfortunately, as often happens, her psychiatrist interpreted the withdrawal symptoms as a relapse of depression or anxiety and reinstated the medication at a higher dose.
Withdrawal vs Relapse
Distinguishing withdrawal from relapse is critical.
Withdrawal symptoms typically begin within days of reducing or stopping medication. They may include:
dizziness
nausea
insomnia
“brain zaps” or electric shock sensations
anxiety and agitation
akathisia
intrusive or violent thoughts
Withdrawal symptoms often improve if the medication is reinstated to the last stable dose.
Relapse, on the other hand, usually develops gradually over weeks or months and mirrors the original emotional presentation prior to medication. It does not reliably improve with rapid dose increases.
Repeated cycles of withdrawal and reinstatement can also contribute to what is known as kindling.
Kindling
Kindling refers to a phenomenon in which repeated cycles of substance use and withdrawal sensitise the nervous system, causing each withdrawal episode to become more severe.
Historically associated with alcohol and benzodiazepines, kindling is now increasingly recognised in psychotropic drug withdrawal. Over time the nervous system becomes more reactive, increasing sensitivity to future reductions and making withdrawal progressively harder to tolerate.
Polypharmacy and Nervous System Overload
By the time Judy came to see me, she was experiencing severe anxiety, cognitive impairment and insomnia.
Her psychiatrist had prescribed propranolol, a beta blocker often used to reduce physical symptoms of anxiety. When Judy reported ongoing insomnia, she was then prescribed olanzapine, an antipsychotic medication commonly used for sedation at low doses.
The olanzapine caused significant morning sedation, so dexamphetamine was added to counteract the grogginess.
At this point, multiple medications with opposing effects were interacting in her system simultaneously:
Cymbalta
Lexapro
propranolol
olanzapine
dexamphetamine
The result was increasing agitation, anxiety and nervous system dysregulation.
If I were to fully explain the pharmacological interactions between these drugs, it would require another article entirely. Suffice to say, it was clear why Judy’s nervous system was in such distress.
Judy’s History
Judy explained that in 2008 she had been working as a social worker in an adolescent mental health unit while raising four adopted children on her own, one of whom was autistic and required intensive care.
She had never married. Work became a way of escaping the overwhelming responsibilities at home.
She also described a childhood in which she had acted as her mother’s confidant and emotional support. Between the ages of 16 and her early twenties she had struggled with anorexia and had previously been prescribed antidepressants.
To manage the overwhelm in adulthood, Judy increasingly relied on red wine. Eventually she entered a detox program, where she met the psychiatrist who first prescribed Cymbalta.
Even before our work together began, Judy had already experienced one failed taper. Following standard pharmaceutical guidelines suggesting that withdrawal effects are mild and self-limiting, her psychiatrist reduced her rapidly from 60 mg to 30 mg.
This history was significant because it suggested a sensitised or “kindled” nervous system. I knew she would likely require a very gradual taper to minimise further harm.
Dependence vs Addiction
The terms dependence and addiction are often used interchangeably, but they describe different phenomena.
Dependence
Dependence is primarily physiological. The body adapts to the presence of a substance and begins to rely on it to function normally.
Characteristics of dependence include:
tolerance
withdrawal symptoms when stopping
neuroadaptation within the nervous system
A person can be dependent without being addicted. For example, someone prescribed opioid medication for severe pain may develop physical dependence without compulsive misuse.
Addiction
Addiction is behavioural and psychological. It involves compulsive use despite harmful consequences.
Characteristics of addiction include:
loss of control
compulsive cravings
continued use despite harm
psychological reliance to manage emotional pain
From an Internal Family Systems (IFS) perspective, addictive behaviours can be understood as protective “firefighter” parts attempting to numb distress or emotional overwhelm.
In Judy’s case, her primary issue was dependence rather than addiction. Her brain had adapted to long-term exposure to psychotropic medication.
The Brain’s Adaptation to Medication
With antidepressants and antipsychotics, the brain adapts to the constant presence of the drug.
The widely promoted “chemical imbalance” theory of depression has been increasingly challenged in recent years. Critics argue that the theory was oversimplified and heavily marketed by pharmaceutical companies.
The brain continually strives for homeostasis. In response to ongoing medication exposure, receptor sensitivity changes and neurotransmitter systems recalibrate.
Over time the nervous system becomes dependent on the presence of the medication.
This is why reducing psychiatric medication can become so difficult.
Hyperbolic Tapering
Judy wanted to discontinue her medication safely. Given her history, I believed she would need to taper hyperbolically.
Hyperbolic tapering involves making progressively smaller reductions as the dose becomes lower.
Rather than reducing linearly — for example by dropping 10 mg each time — reductions become increasingly gradual near the end of the taper.
For example:
40 mg → 20 mg
20 mg → 10 mg
10 mg → 5 mg
5 mg → 2.5 mg
Another common approach is reducing by approximately 10% of the previous dose and holding for periods of stabilisation between reductions.
Why Hyperbolic Tapering Matters
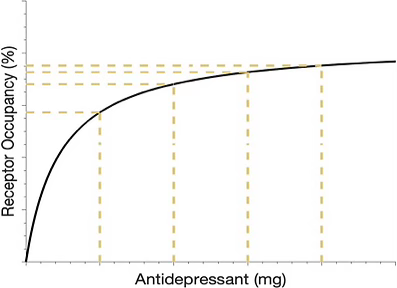
Research using receptor occupancy studies suggests that even low doses of antidepressants can occupy a very high percentage of brain receptors.
This means that small reductions at lower doses may have disproportionately large effects on the nervous system.
In practice, this is why dropping from 5 mg to zero can feel far more destabilising than reducing from 40 mg to 35 mg.
Psychiatrists and researchers such as Mark Horowitz and David Taylor discuss this extensively in The Maudsley Deprescribing Guidelines (2024). Anders Sørensen also explores these principles in Crossing Zero (2025).
The Emotional Dimension
Judy had spent much of her life moving away from painful emotions through work, wine and eventually medication.
This is profoundly human. Most of us seek relief from emotional pain.
However, tapering medication often means that long-suppressed emotions begin to surface again.
The therapeutic task is not simply medication reduction. It is helping the client build the capacity to tolerate and understand difficult emotional and bodily experiences.
Antidepressants can dampen emotional intensity, but they do not resolve the underlying life experiences, attachment wounds or unresolved trauma contributing to suffering.
Judy had never truly stopped to examine:
why she adopted four children while still very young and living at home
why she developed anorexia at sixteen
why she relied so heavily on work and caretaking
why she felt unable to tolerate stillness or emotional discomfort
Eventually, her attempts to numb overwhelm resulted in dependence on a complex medication regimen that caused significant iatrogenic harm.
A Kindled Nervous System
Judy’s tapering journey has been difficult.
Despite collaborative planning with her integrative doctor and myself, she struggled to follow the tapering schedule consistently. Feeling temporarily stable after an initial reduction, she reduced again too quickly.
Her nervous system reacted intensely.
Once a nervous system becomes highly sensitised or kindled, even minor changes — including supplements or seemingly benign medications — can trigger significant symptoms.
At that point, there is often no medication that can simply “fix” the problem. The work becomes learning how to gradually tolerate and regulate bodily sensations rather than constantly escaping them.
Judy also developed cognitive difficulties after multiple medication changes and additions.
Compounding matters further, her partner responded with frustration and criticism rather than emotional safety. From an attachment perspective, this lack of safety likely amplified her nervous system distress.
When overwhelmed, Judy repeatedly sought reassurance from her psychiatrist, whose primary response was further medication changes.
As the saying goes: when your only tool is a hammer, every problem begins to look like a nail.
The Role of Counselling
My primary focus with clients withdrawing from substances or psychotropic medications is resourcing.
In practical terms, this means helping them find even brief moments of safety, steadiness or calm within the body and mind.
Only when the nervous system has some degree of stability can deeper therapeutic work occur.
The goal is not merely to remove medication, but to help clients understand themselves more deeply rather than relying solely on substances or compulsive behaviours to manage distress.
Judy’s story is ongoing.
I hold hope for her because I have seen many people successfully taper from psychiatric medication when the process is gradual, collaborative and carefully supported.
I am one of them.
Her story highlights both the potential dangers of rapid psychotropic withdrawal and the importance of compassionate, informed care.
While her experience is extreme, it is not hopeless.
Every tapering journey is individual. With appropriate pacing, support and nervous system regulation, many people can successfully reduce or discontinue psychiatric medication.
References
Horowitz, M., & Taylor, D. (2024). The Maudsley Deprescribing Guidelines. Wiley Blackwell.
O’Brien, C. P., Volkow, N., & Li, T.-K. (2006). What’s in a word? Addiction versus dependence in DSM-V. American Journal of Psychiatry, 163(5), 764–765.
Sørensen, A. (2025). Crossing Zero. North and Vale.
In his book ‘Crossing Zero’ (2025), Anders Sorenson explains the receptor occupancy/dose relationship. For example, at only 20mg of Prozac – 86% of the brain’s receptors are occupied with serotonin from the drug. This means that the smaller the dose the greater the impact it has on the brain. Mark Horowitz and David Taylor also describe this in their comprehensive book ‘The Maudsley Deprescribing Guidelines’ (2024)
Whitaker, R. (2010). Anatomy of an Epidemic. Crown Publishing Group.
In his book “Anatomy of an Epidemic” (2010) Robert Whitaker summarises a World Health Organisation study (1998) showing that people diagnosed and treated with psychiatric medication for depression had worse outcomes than those not exposed to drugs.
Mark Horowitz interview on withdrawal, relapse and hyperbolic tapering:
In this interview Mark Horowitz discusses the difference between withdrawal and relapse, the effects of long-term antidepressant use and the role of clinicians and peer support in de prescribing and hyperbolic tapering.